
01 / THE ARGUMENT
The lower purchase price is the beginning of the decision
A biologic procurement team can report a favorable acquisition price while the payer sees a smaller saving and the patient sees no improvement at all. My thesis is that biosimilar adoption should be governed as a value-sharing decision. The executive objective is a clinically appropriate treatment pathway that remains attractive to the provider, affordable within the benefit and dependable through the supplier contract. A purchase-price dashboard measures only one part of that system.
The scientific boundary matters. FDA describes an approved biosimilar as highly similar to its reference product, with no clinically meaningful differences. Interchangeability concerns pharmacy-level substitution and remains subject to state law; it does not establish a superior clinical effect. Those distinctions support clear prescribing and patient communication. They do not establish what any specific plan, hospital or patient will save. [1]
02 / THE ARGUMENT
A 2026 study makes the distribution of value visible
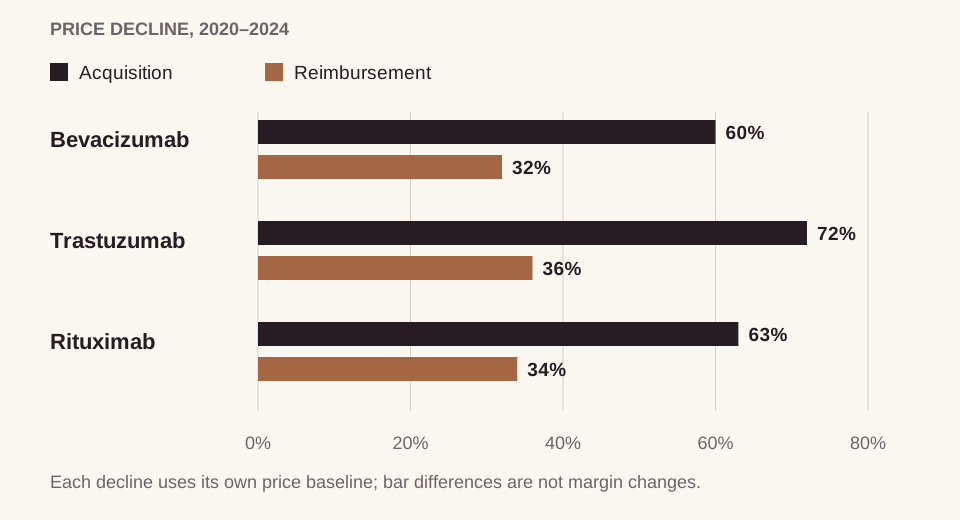
Robinson, Kosorukov and Whaley examined 66,139 patients receiving oncology biologics or biosimilars in 1,541 hospitals. Between 2020 and 2024, acquisition prices for biosimilars of bevacizumab, trastuzumab and rituximab declined 60%, 72% and 63%; insurer reimbursement declined 32%, 36% and 34%. Biosimilar shares reached 93%, 87% and 84%. The March 2026 JAMA study therefore documents growing hospital markup margins alongside adoption. It does not prove that margin changes caused adoption or measure clinical superiority. [2]
My interpretation is that the contract determines whether competitive pricing becomes a shared improvement or a redistribution within the existing chain. A payer seeking a larger reduction and a provider seeking a sustainable service line can both be rational. Negotiation should disclose acquisition cost, realized reimbursement, patient liability and implementation expense separately. A single aggregate saving obscures the disagreement that later reappears as formulary friction.
Acquisition prices fell faster than reimbursement.
 View full-size exhibit ↗
Source & method. Observed decline magnitudes from each price measure’s own 2020 baseline, 2020–2024. These are different bases; subtracting the declines does not give a change in margin percentage points. Observational data from 66,139 patients in 1,541 hospitals do not establish causality.
03 / THE ARGUMENT
Benefit design and procurement need one decision ledger
A 2024 multistakeholder commentary by Sullivan and colleagues identifies price volatility, reimbursement incentives and rebate complexity as threats to a sustainable US biosimilar market. These are stakeholder perspectives from a roundtable, rather than a causal estimate of any individual contract's performance. [3] I would translate the concerns into a ledger that reconciles the medical and pharmacy benefit for each product, indication, route and site of care.
The proposed ledger would include acquisition cost after applicable concessions; expected reimbursement under the actual contract; patient cost sharing under the actual benefit; approved-product and indication checks; authorization lead time; inventory exposure; and the time required to change ordering, dispensing and administration systems. Finance should distinguish a rebate forecast from a settled rebate. Clinical leadership should approve the treatment pathway and exceptions. Procurement should document available alternatives and supplier commitments before committing volume.
04 / THE ARGUMENT
New competition increases the need for disciplined conversion
On October 2, 2026, Fierce Pharma reported an expanded Teva–Samsung Bioepis agreement for up to six biosimilar candidates, dividing development and manufacturing responsibilities from commercialization. This is an attributed pipeline and partnership signal. Candidates and announced agreements are not equivalent to approved, launched or locally available products. [4]
My proposed conversion process starts with a small, defined patient cohort and an approved clinical protocol. The team verifies product availability and coverage, updates the order set, explains the change to patients, and reconciles the first completed claims. An exception pathway should remain available when clinical circumstances, benefit restrictions or supply make the intended option unsuitable. The operating test is whether a clinician can complete appropriate treatment without repeated administrative rework. Expansion should follow completed-case evidence rather than the size of the announced discount.
05 / THE ARGUMENT
A sustainable contract needs a distribution rule and an exit rule
I would ask a provider–payer negotiating team to specify the distribution of incremental value before a wider conversion: the payer's expected net reduction, the provider's viable contribution after administration costs, and the patient's expected liability. The mechanism could be a revised unit reimbursement, a pathway payment or another lawful arrangement reviewed against the parties' circumstances. None should assume that a published average margin applies to the local organization.
A durable strategy also prices the cost of changing course. A temporary acquisition discount can justify a conversion yet become less attractive after a reimbursement change, rebate settlement or supply interruption. The provider may bear inventory and workflow costs before the payer realizes its reduction. I would therefore agree the review period, the evidence used to reconcile value and the circumstances that permit renegotiation or a clinically appropriate alternative.
The investment committee should compare the immediate contribution with the dependence being created: supplier concentration, contract duration, inventory exposure and the effort required for a second conversion. Preserve enough flexibility to respond when realized costs, coverage, supply or patient experience depart from the underwriting assumptions. The contract should make a viable care pathway renewable; a favorable opening discount is only one input to that decision.
FROM EVIDENCE TO ALLOCATION
The operating and investment case
My proposed operating design. These decisions and evaluation criteria are not outcomes established by the cited studies.
- Decision
- Approve a bounded biosimilar pathway and an explicit payer–provider value-sharing agreement for one clinically governed service line.
- Accountable owner
- Pharmacy director and service-line medical director, with the CFO, payer contracting lead and procurement lead jointly accountable for the economic reconciliation.
The delivery sequence
- Establish a reference-period cohort with product, indication, benefit, site and realized claim economics.
- Verify FDA approval, coverage, supplier availability and clinically authorized exceptions.
- Negotiate the distribution of savings and update prescribing, authorization, inventory and administration workflows.
- Reconcile completed treatment episodes, patient liability and actual concessions before expanding volume.
The economics
My proposed calculation: provider contribution equals realized reimbursement less net acquisition and incremental delivery costs; payer net reduction equals baseline net episode spending less new net episode spending and implementation costs. Report patient liability separately and include all applicable rebates consistently in both periods. The ledger must avoid counting the same price reduction as both payer saving and provider margin improvement. Published oncology associations are not a local ROI forecast.
The measures that govern expansion
- Eligible completed episodes by product and benefit
- Realized net spending per comparable episode
- Patient liability and treatment delays
- Provider contribution after implementation expense
- Supplier fill performance and avoidable inventory loss
Stop or redesign when
Pause expansion if the pathway generates clinically inappropriate changes, deteriorating access, unreliable supply, unreconciled rebates or patient liability above the agreed guardrail. Recalculate the contract before increasing volume.
THE EVIDENCE LEDGER
What supports the argument
Study findings, policy requirements and market signals support different claims. Their boundaries remain visible.
[1] policy · Undated; accessed 2026-10-07
Biosimilars Basics for Patients
- Design or status
- Official regulatory educational material
- Verified finding
- FDA explains that approved biosimilars have no clinically meaningful differences from their reference products and that pharmacy-level substitution of interchangeable products is subject to state law.
- Boundary
- An approval and educational explanation establish the regulatory meaning of biosimilarity, not product-specific coverage, commercial availability or patient savings.
[2] peer-reviewed · March 11, 2026
Hospital Adoption and Pricing for Oncology Biosimilars
- Design or status
- Observational study linking commercial insurance, hospital acquisition prices and hospital characteristics, 2020–2024
- Verified finding
- In 66,139 patients at 1,541 hospitals, acquisition prices fell faster than reimbursement prices for three oncology biosimilars, increasing hospital markup margins while biosimilar use rose.
- Boundary
- Associations cannot establish causal effects of margin changes. Commercially insured oncology cases do not establish pharmacy-benefit, Medicaid or patient-level savings. The article's Discussion was corrected June 29, 2026; this analysis uses the reported abstract results.
[3] peer-reviewed · July 16, 2024
Stakeholder perspectives on the sustainability of the United States biosimilars market
- Design or status
- Commentary by participants in a December 2023 multistakeholder roundtable
- Verified finding
- Participants identify volatility, reimbursement incentives and complex rebate structures as barriers to sustainable biosimilar competition.
- Boundary
- Stakeholder commentary provides a proposed policy interpretation; it is not an independent causal evaluation or a representative survey of the US market.
[4] market · October 2, 2026
Teva, Samsung Bioepis deepen bonds in pact for up to 6 new biosimilars
- Design or status
- Trade reporting on an announced commercial development agreement
- Verified finding
- The report describes a partnership covering up to six potential candidates, with Samsung Bioepis handling development, regulatory work and manufacturing and Teva handling commercialization if approved.
- Boundary
- A deal announcement does not establish approval, launch timing, realized competition or a buyer's savings.
FOLLOW THE SOURCE
Sources and editorial method
Selected evidence was reviewed through October 7, 2026. Numbered references connect claims to their underlying records. Economic mechanisms and business cases are my analysis unless a source is cited. The review is selective; publication dates retain the precision available in the source.
Biosimilars Basics for Patients
U.S. Food and Drug Administration. FDA. Undated; accessed 2026-10-07. policy.
Hospital Adoption and Pricing for Oncology Biosimilars
James C. Robinson, Ari D. Kosorukov, Christopher M. Whaley. JAMA. . peer-reviewed.
Stakeholder perspectives on the sustainability of the United States biosimilars market
Sean D. Sullivan, Sophia Z. Humphreys, Davide Fox, Catherine M. Lockhart, Ashley Tait-Dinger, J. D. Betancourt, Kenneth M. Komorny, Ryan Haumschild, Barry Chester, Matthew Harman, Joshua A. Roth. Journal of Managed Care & Specialty Pharmacy. . peer-reviewed.
DOI: 10.18553/jmcp.2024.24104 · Primary verification record · Consensus paper record
Teva, Samsung Bioepis deepen bonds in pact for up to 6 new biosimilars
Fraiser Kansteiner. Fierce Pharma. . market.
Study authors retain credit for their work. Researcher affiliations and publisher names do not imply affiliation with or endorsement of this analysis.