












Healthcare executives should read the 2026 investment conversation as a debate over where capital can change the cost or reliability of care. The useful connecting question is who controls access, operational throughput, and payment. That framing reaches beyond AI into employer benefits, medicines, diagnostics, staffing, home care, and the systems joining them. The following interpretation combines distinct investor and analyst perspectives; it is neither a statement of consensus nor clinical evidence.
Capital is not expressing one uniform healthcare thesis. PitchBook's August public listings pair a cautious healthcare services outlook with a healthcare IT headline describing deal activity on a record-setting pace. These are different markets, and the inaccessible underlying reports prevent a detailed comparison. Still, the contrast is a useful executive prompt: a company's ability to attract buyers does not answer whether the care organization using its product has investment capacity. Procurement decisions should therefore include vendor ownership, integration plans, continuity, and future pricing, alongside immediate functionality. This is a diligence implication, not a finding from the reports.
The workflow opportunity is similarly wider than automating documentation. YC's Fall 2026 request on aging focuses attention on coordination, monitoring, accessible interfaces, and assistance at home. For an operator, the unit of analysis should be the entire journey: who notices a problem, who responds, which appointment is arranged, and whether information reaches the next caregiver. A product can make one step faster while shifting work elsewhere. Useful evaluation would therefore examine response times, missed handoffs, caregiver burden, and avoidable escalation, while recording implementation cost and the staff capacity needed to support the service.
Payment and distribution determine who can capture that value. a16z's September employer-plan thesis points toward challenger insurers, PBMs, and infrastructure businesses competing for benefit spending. Its January discussion also raises the possibility of more consumer purchasing outside insurance. Read together, these arguments suggest examining both the purchaser and the user. Employer savings, member affordability, provider reimbursement, and the vendor's revenue need not move together. A purchasing process should ask which party carries clinical and financial risk, how patients reach appropriate care, and whether a lower headline fee merely relocates costs.
Pharmacy and life science infrastructure belong in the same discussion. Morningstar's Cigna note distinguishes insurance margin progress from a PBM transition; its life science outlook anticipates a profit recovery after a prolonged reset. These perspectives direct attention to established businesses, purchasing channels, and operating cycles that can shape value even without a new consumer application. The executive question is how contracting, purchasing power, supply capacity, and reimbursement distribute the economic benefit. Equity forecasts remain forecasts, and a company's margin recovery alone cannot establish better access or lower costs for patients.
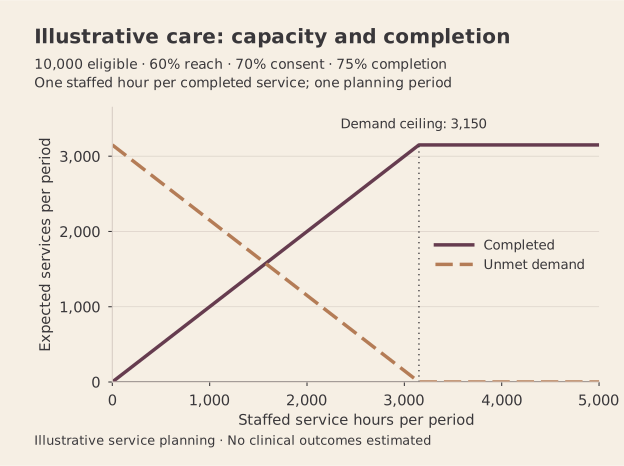
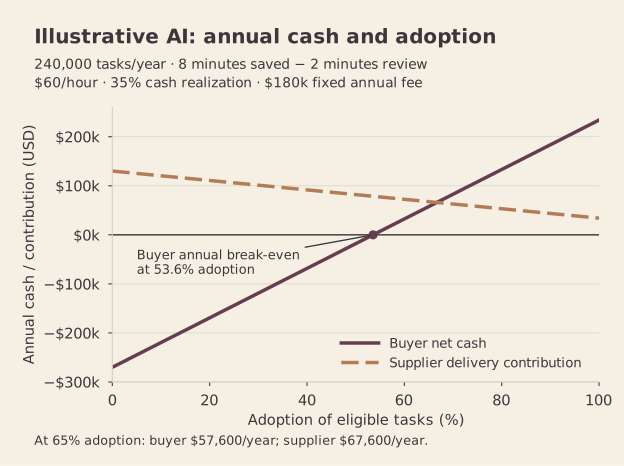
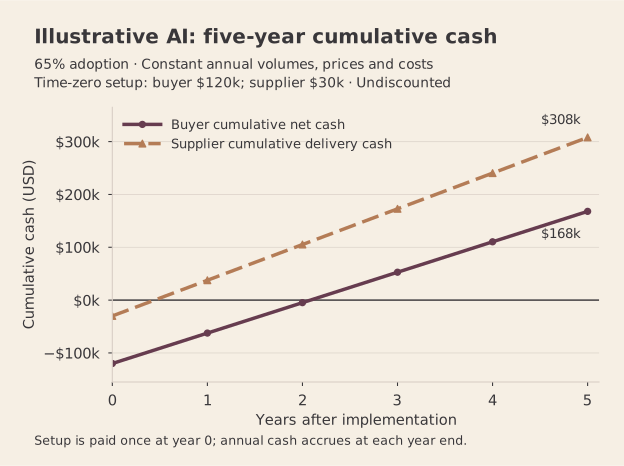
I would make the investment committee reconcile three accounts before approving expansion: the work that changes, the cash the institution can retain and the effect on access or care. Freed minutes require a staffing or throughput decision. Accelerated payment requires a reconciliation of timing, disputes and rework. Additional demand requires funded capacity. An attractive vendor market does not resolve any of those obligations for the purchaser.
Finally, cheaper tasks do not automatically mean a cheaper system. a16z's February care-pricing argument explicitly connects expanded capacity with payment design. An executive can use that hypothesis to test utilization, downstream resource use, and outcomes together rather than assume that unit-cost reductions become net savings. Funding momentum, attractive margins, startup enthusiasm, and valuation estimates can identify questions worth investigating. They cannot establish clinical safety, effectiveness, equity, or causal savings. Those claims require appropriate primary studies and local evaluation with relevant comparators, patient populations, follow-up, and the full cost of implementation.
Market sources and access scope
- a16z · Employers Are Shopping for a New Health Plan — 2026-09-10. Investor thesis. First-party full article retrieved. An investor's proposed market opportunity, with commercial interests. The article does not establish that challengers outperform incumbent plans or that automation improves clinical outcomes.
- a16z · Infinite Healthcare: What’s It Worth? — 2026-02-26. Investor thesis and economic scenarios. First-party full article retrieved. Prospective economic argument with illustrative scenarios, not a measured demonstration that AI reduces total healthcare spending or improves population health.
- a16z · Healthcare 2026: AI Doctors, GLP-1s, and Insurance Defection — 2026-01-27. Investor and industry commentator discussion. First-party episode description retrieved; audio not independently transcribed. Summary of a discussion rather than a population-level utilization study. No claim that cash payment is appropriate or accessible for every patient.
- Y Combinator · Requests for Startups — Fall 2026: AI for the Aging Population — Fall 2026. Startup opportunity request. Fall 2026 edition reviewed. This is an invitation to founders, not a market-size validation or clinical study. My analysis uses the opportunity framing; it does not rely on the page’s demographic or caregiver figures.
- PitchBook · Healthcare Services Report: Gusting Macroeconomic Headwinds Impede Progress — 2026-08-14. Private market research; public report listing. Public title, date and report scope reviewed; the full report was unavailable. My interpretation is limited to that listing and does not rely on detailed deal counts, return forecasts or findings about patient outcomes.
- PitchBook · Healthcare IT PE Update: Deal Counts on Pace to Surpass 2021 Record — 2026-08-17. Private market research; public report listing. Public title, date and report scope reviewed; the full report was unavailable. The headline describes an estimated pace, not a completed annual result. The underlying sample and methods could not be assessed.
- Morningstar · Cigna Earnings: Medical Insurance Margin Progress Constrained by PBM Business Model Transition — 2026-07-30. Equity analyst note; public indexed excerpt. Public title, date and excerpt reviewed; the full article was unavailable. This company-specific investment analysis does not establish patient drug costs, clinical outcomes or a sector-wide PBM trend.
- Morningstar · After a Long Reset Period, Life Science Stocks Look Set to Rebound — 2026-03-23. Equity analyst outlook; public indexed excerpt. Public excerpt and publication date reviewed; the full article was unavailable. Profit expectations and valuations are forecasts, not evidence of therapeutic effectiveness or a completed industry recovery.