
Start with the unresolved medication decision
Pharmacy strategy begins by identifying what prevents a person from carrying out the agreed treatment plan. The barrier may involve clinical appropriateness, contradictory instructions, affordability, a benefit restriction, dispensing, language or the person’s own preference. The response should match that barrier and identify who has the authority to resolve it.
I would organize the pathway around the next decision and the professional authorized to make it. A coordinator can resolve an access exception. A pharmacist can review the regimen within scope. A prescriber can change treatment. The operating system should connect those actions without confusing their authority.
Read the evidence beyond the savings headline
My investment conclusion is to specify the benefit being purchased. Medication safety, patient understanding and a more reliable transition can justify a service even when a readmission claim is unsupported. Those benefits need their own measures, staffing requirements and price. A null utilization result should improve the investment thesis rather than disappear from it.
Build the four linked workstreams
| Workstream | Operating question | Completion evidence |
|---|---|---|
| Appropriateness | Is the intended regimen reconciled with clinical judgment and the person’s goals? | A reviewed medication plan and ownership of unresolved discrepancies. |
| Access | Can the person obtain the intended therapy through a viable benefit and delivery route? | The access barrier is resolved or a clinically appropriate alternative is considered. |
| Use and understanding | Can the person explain and implement the agreed plan? | A meaningful conversation, appropriate support and confirmation of remaining difficulties. |
| Monitoring | Who acts on nonresponse, possible harm or a changing regimen? | An agreed follow-up and a documented clinical response when needed. |
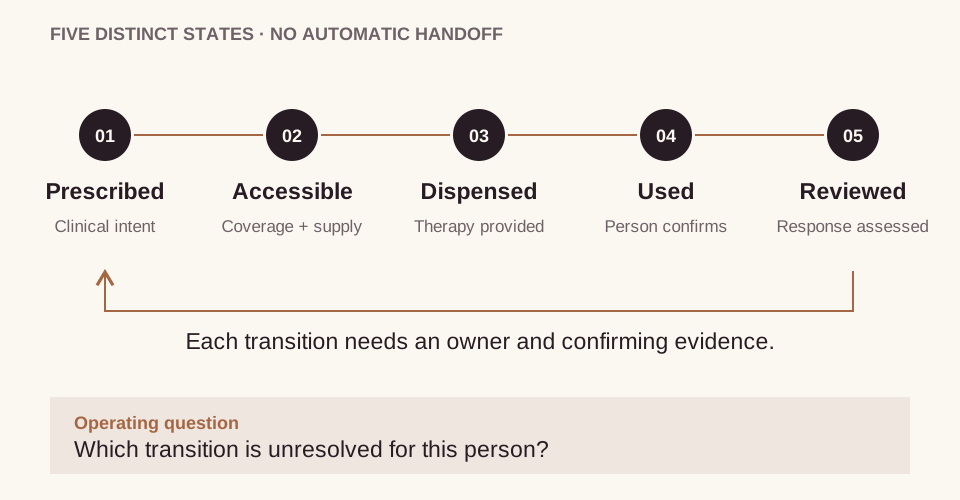
I would keep prescription, dispensing, claim payment, possession, use and response as separate states. A claims-derived adherence measure is an operational proxy; it cannot establish why a gap exists or whether continuing a medicine is clinically appropriate. The person’s explanation and the clinical record remain necessary.
A prescription is the start of a pathway.
 View full-size exhibit ↗
Source & method. My proposed pathway synthesis from the article’s four workstreams: appropriateness, access, use and understanding, and monitoring. The sequence is a conceptual service map, not a measured patient funnel; step numbers indicate order only.
Make deprescribing a care process
My strategic position is that the target should be appropriate treatment with an agreed monitoring plan. Paying for discontinuation volume can create the wrong incentive, just as rewarding dispensing volume alone can. The pathway needs patient agreement, prescriber accountability, communication across settings and a way to revisit the decision.
Reconcile the economics across the benefit boundary
For a payer, medical and pharmacy spending are connected but cannot be netted together through an assumed offset. For a pharmacy or clinical service business, revenue depends on the actual contract, acquisition and delivery cost, workforce, payment adjustments and cash timing. For the person, out-of-pocket expense and practical access may dominate the decision. I would show all three views.
A proposed service contribution model is contracted service revenue minus pharmacist and support labor, technology, follow-up and allocated operating cost. Drug economics belong in a separate ledger when the business also dispenses. Shared-savings payments require their own settlement bridge. Mixing these streams makes a profitable transaction look like a proven health benefit.
The funding agreement should make the professional obligation durable when the dispensing economics change. If clinical follow-through is implicitly subsidized by drug margin, a shift in payer terms or therapy mix can weaken the service just when patients still need it. I would identify which responsibilities have explicit payment, which depend on cross-subsidy and whether the business can sustain those commitments under a less favorable mix.
Medicare Part D medication therapy management has a defined program framework and annual sponsor requirements. That framework is one possible operating context, not a universal payment entitlement for every pharmacy activity. Contract-year requirements and the specific agreement must determine the delivery and revenue model. [3]
The executive decision
I would fund the pharmacy capability that resolves the most consequential break in the care pathway, then test it under real operating conditions. The scorecard should show access, clinically reviewed discrepancies, patient experience, follow-up, workforce burden and full delivery cost. Any claim about hospital use or total spending needs an appropriate comparator.
A dependable pharmacy service makes the medication decision, next owner, patient access and unresolved work visible across the care team. That shared record allows leaders to invest in the specific clinical or operational capacity required to complete the pathway.
Sources and scope
Selected primary studies and official references reviewed September 27, 2026. Research findings are attributed to their authors. The operating proposals and strategic interpretations are my synthesis; I present them as proposed designs rather than a tested bundle or a personal implementation record.
- Pevnick et al. Pharmacist-Led Discharge Care to Reduce Postdischarge Health Care Utilization. JAMA Network Open, March 17, 2026.
- Baas et al. Deprescribing in older patients with hyperpolypharmacy. Age and Ageing, July 19, 2026.
- CMS. Medication Therapy Management program information and annual guidance. Reviewed September 27, 2026.