
Move from available appointments to accountable treatment
My strategic question is whether someone notices when a person does not improve and has the authority and capacity to change the plan. A provider directory, a completed screen or a telehealth appointment does not answer that question. Integration requires a recurring way of reviewing the population, identifying unfinished work and making an appropriate next decision.
I would define the population, the clinical scope and the intended outcomes before choosing the platform. Depression alongside chronic physical illness, a severe mental illness pathway and substance-use care may need different teams, response times and service networks. A common coordination layer can support them; it should not flatten those differences into one generic engagement journey.
Use the research at the right level of certainty
My interpretation is that organizational design deserves an explicit investment case. The intervention is more than software: it includes people, review processes, treatment access and the ability to respond. The value thesis should name those components and evaluate the relevant outcomes rather than claiming that integration automatically lowers total medical spending.
Design the population review cycle
| Capability | What management must fund | What the clinical team decides |
|---|---|---|
| Population registry | Reliable enrollment, contact information, permissions and overdue-action tracking. | Who is appropriate for the pathway and what information is clinically relevant. |
| Care management | Time for engagement, follow-up, measurement and coordination. | How the person’s goals, symptoms and functioning inform treatment. |
| Specialist support | Protected review capacity and a reliable route to consultation. | When to adjust treatment or move to another level of care. |
| Continuity | Maintenance contacts, re-entry and communication across settings. | How to respond to nonresponse, deterioration or changing preferences. |
The registry should make nonresponse visible without turning people into compliance scores. A missed contact may reflect preference, a technical barrier, work demands, unstable access or an unsuitable service. The team needs a respectful route to clarify the reason and revise the plan.
Behavioral-health capacity includes the review cycle.
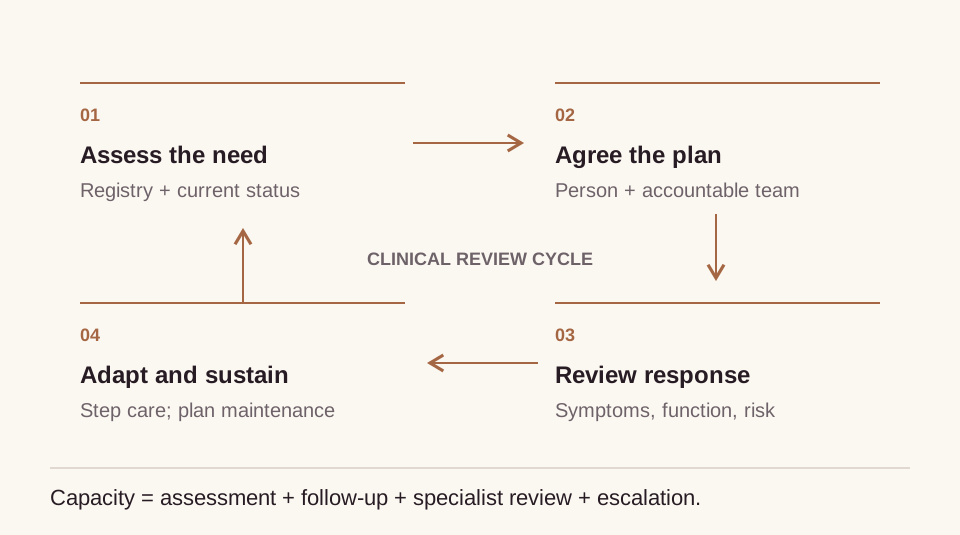 View full-size exhibit ↗
Source & method. My proposed service design informed by the article’s evidence review. Arrows describe a review cycle rather than a fixed clinical protocol. Assessment, follow-up, specialist review and escalation are distinct demands on capacity.
Budget for what happens after the initial benefit
My operating conclusion is to include maintenance, reassessment and re-entry in the service design. An initial episode can end while the person still needs a practical way back into care. If the financial model pays only for the first engagement, the clinical and economic objectives may diverge exactly when sustained support matters.
Price capacity and protect the clinical boundary
I would estimate staffing from the actual work: new assessments, active follow-up, specialist review, documentation, language support and escalation. A nominal panel size tells little without that workload. The service should show the hours required per period, the mix of work and the queue that forms when capacity is insufficient.
For the financial case, I would model the active population as a stock of continuing obligations. New enrollment adds assessment and treatment work; response, transfer, maintenance and re-entry change the mix of subsequent work. A service that sells additional covered lives faster than it develops clinical capacity can accumulate an unfunded queue even when its revenue grows. The financial review needs the expected workload per period and a funding route for the people already accepted.
Contracted revenue, collection and total delivery cost should then be reconciled against that workload. Retention and additional appointments describe the business; symptom change, function, access and patient experience describe the care. Neither account replaces the other. Expansion is supportable when the organization can sustain the clinical obligation and the purchaser has explicitly funded the value being sought.
AI can help organize records, identify an overdue administrative task or draft material for review. The treating team retains diagnosis, treatment and escalation decisions. A service must describe its actual response coverage rather than letting an always-available interface imply continuous clinical care.
The leadership test
Before expanding, I would ask whether the team can explain who is improving, who is not being reached, who needs a different approach and which constraint prevents that response. The answer should be visible by relevant population groups without exposing unnecessary personal information.
An integrated behavioral-health business earns its position through a reliable treatment system. Its strategic asset is the combination of trusted access, clinical judgment, continuity and a delivery model that can sustain the work.
Sources and scope
Selected primary studies and official references reviewed September 27, 2026. Research findings are attributed to their authors; the operating proposals and strategic interpretations are original synthesis. This article does not claim that these proposals constitute a tested bundle or personal implementation record.
- Sweeney et al. Primary care and community interventions for multimorbidity involving depression or anxiety. BMJ Medicine, April 10, 2026.
- Williams et al. Longer-term effects of modernized collaborative care for depression on multiple mental health factors (eIMPACT). Journal of Affective Disorders, January 2026 issue; online September 8, 2025.